
PDF-ADULT Patient Questionnaire
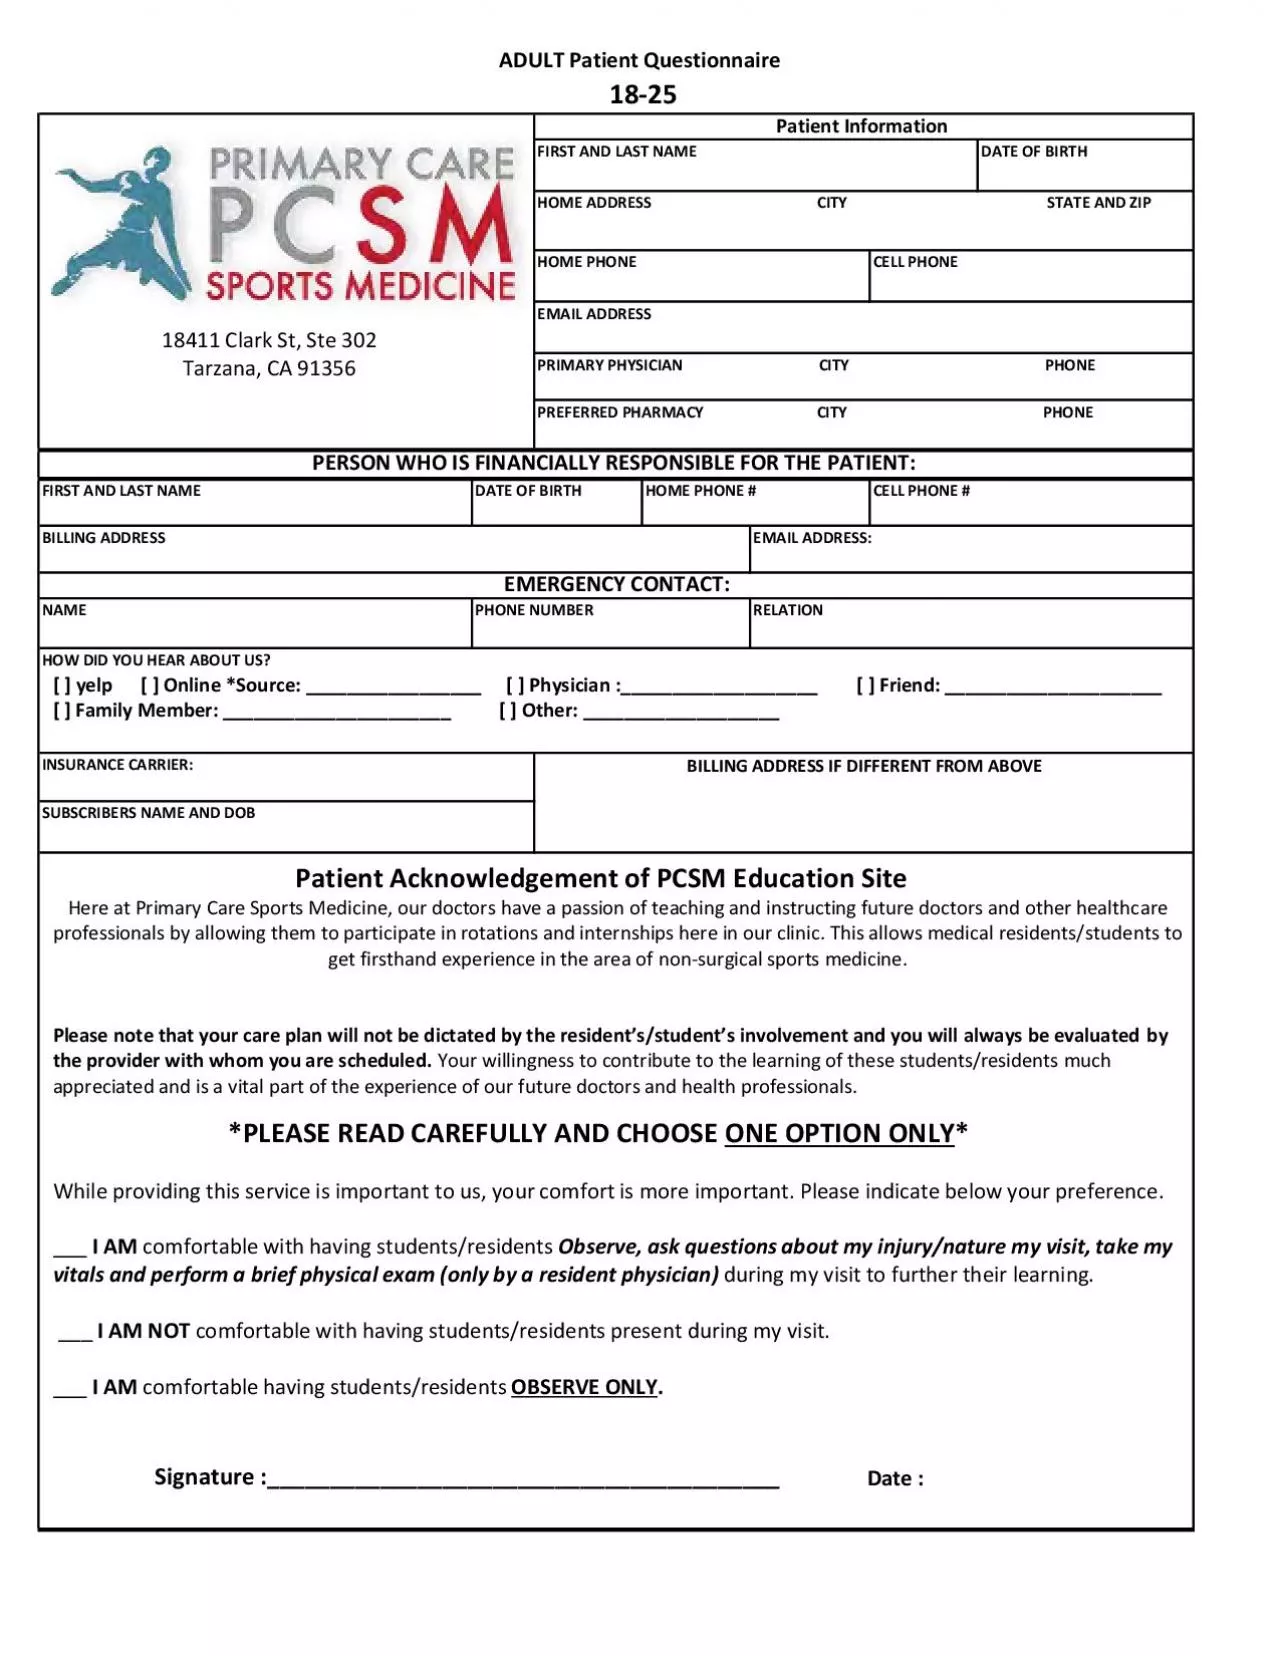
1825 BILLING ADDRESS EMAIL ADDRESSEMERGENCY CONTACTNAMEPHONE NUMBERRELATIONINSURANCE CARRIERBILLING ADDRESS IF DIFFERENT FROM ABOVESUBSCRIBERS NAME AND DOB HOW DID
Download Presentation
Download Note : "ADULT Patient Questionnaire" is the property of its rightful owner. Permission is granted to download and print materials on this website for personal, non-commercial use only, provided you retain all copyright notices. By downloading content from our website, you accept the terms of this agreement.
Presentation Transcript
Transcript not available.